ELWA Hospital Under Spotlight …As Two Patients Left Waiting Without Healthcare
Health |
👁 1 Views
|
October 06, 2026
MONROVIA: it seems authorities at the Ministry of Health are doing little or nothing to reverse the alarming situation at various health facilities, as it relates to demanding money before treatment.
Multiple reports from ordinary citizens indicate that health administrators have instituted a policy for patients to pay health related fees before they can be allowed in health facilities for treatment.
Some facilities, according to reports, demand generally high and /or unaffordable fees to be deposited before working on patients.
According to many commentators, such unprofessional practice may have contributed to the death of several sick persons.
Although, the fees are varied, the health facilities don’t compromise their policy of “PAY AS YOU COME FOR TREATMENT.”
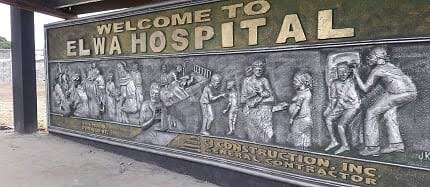
A case in point recently occurred at one of the country’s leading hospitals, ELWA, located in Paynesville.
A troubling account from the ELWA hospital has brought renewed attention to the anguish which families face when critically ill patients arrive at health facilities seeking urgent medical intervention but encounter delays, uncertainty, or what other members of the public perceive as indifference.
As Liberia observes October as the Month of Good Governance, a disturbing late-night experience at ELWA Hospital has renewed concerns about emergency care, patient attention, accountability, and compassion.
The experience was narrated by Nicholas S. Mulbah, who said, he spent the late hours at ELWA Hospital in Paynesville, outside of Monrovia, after rushing a sick member of his school staff to the facility.
According to Mulbah, what began as an emergency visit quickly turned into an emotionally devastating experience when, within less than an hour, he witnessed two patients died under circumstances that left him deeply shaken and brokenhearted.
“It is 11:41 p.m., and I am at ELWA Hospital because a staff member of my school fell ill, and we rushed him to the hospital,” Mulbah wrote in an account circulated publicly.
According to him, during the following two hours, he witnessed two separate emergency cases that raised serious questions in his mind about the responsiveness of emergency services and the urgency with which vulnerable patients are handled.
In the first incident, Mulbah said, a black SUV arrived at the hospital compound carrying a patient. And observed someone approached the vehicle, checked the patient’s blood pressure and communicated over a radio. The patient reportedly remained inside the vehicle for some time before being pronounced dead.
Minutes later, according to Mulbah, a kehkeh (tricycle) arrived carrying another man, not named, who had reportedly collapsed elsewhere.
The kehkeh rider, Mulbah said, explained that he had found the man after his collapse and brought him to the hospital for medical assistance. There was reportedly no relative accompanying the patient, Mulbah narrated.
According to him, the man remained in the kehkeh and subsequently reported dead, with relatives arriving only after they had been contacted and informed of his demise.
The account has prompted a broader question that extends beyond one hospital or one night: what happens when critically ill people arrive at health facilities without money, relatives, influence, or someone to speak on their behalf?
Mulbah himself acknowledged that he did not know all the medical circumstances surrounding the two deaths and could not determine what interventions were medically possible.
But, he stressed that the incidents warranted institutional review, particularly regarding emergency response.
His concern is particularly significant as Liberia observes October as the Month of Good Governance—an occasion intended to place accountability, institutional performance, transparency, public service, and citizen welfare at the center of national discussion.
Good governance, however, does not begin and end in government offices.
It is also experienced at hospital reception desks, emergency rooms, pharmacies, laboratories, outpatient departments, maternity wards and treatment rooms, where citizens encounter the State and public-service institutions at some of the most vulnerable moments of their lives.
For a frightened family rushing a loved one to a hospital, a delay can feel like abandonment.
For a patient struggling to breathe, suffering severe pain or losing consciousness, every minute can matter.
And for a person brought to a hospital by a stranger, the absence of a relative should not automatically mean the absence of urgent attention.
Mulbah’s experience, has therefore, triggered a call for health-facility administrators—particularly those responsible for public and donor-supported institutions—to strengthen supervision of emergency services and ensure that patients receive timely assessment and appropriate care.
Concerns about patient care in Liberia have, over the years, included complaints about long waiting periods, overcrowded facilities, shortages of medicines and equipment, inadequate staffing, communication gaps and the conduct of some health workers.
Such concerns should be investigated institution by institution rather than generalized to all nurses, doctors or medical practitioners.
Yet, the complaints are serious enough to demand stronger administrative oversight.
Hospital administrators should know what happens inside their facilities after regular working hours.
They should monitor emergency response systems, patient triage, staff attendance, professional conduct, medication availability, referral procedures and the handling of critical cases, said Teah Wilson, a resident of central Monrovia.
They should also ensure that nurses, doctors and other health professionals remain focused on patient care while on duty, Wilson indicated.
Allegations that some health workers spend excessive time on personal social-media activities while patients wait for attention should be thoroughly investigated where reported, rather than ignored by hospital authorities.
Patient care must remain the first responsibility of every health professional on duty, a medical advocate added.
Equally troubling, are concerns surrounding the availability and handling of medicines.
Donated medicines and medical supplies are provided to strengthen Liberia’s health system and ensure that vulnerable citizens can access essential treatment.
They are not commodities to be diverted, privately sold or withheld from patients who need them in hospitals and other medical centers across the country.
Health authorities, must therefore strengthen pharmaceutical accountability, including inventory controls, dispensing records, stock monitoring and regular audits to determine where medicines originate, where they are stored, who receives them and how they are distributed, a medical practitioner who preferred not to be named in print strongly suggested.
According to her, where allegations of illegal sale or diversion of government- or donor-provided medicines arise, the appropriate authorities should investigate and, where wrongdoing is established, apply the law.
The October governance observance should consequently provide more than speeches, banners and public ceremonies.
“It should become an opportunity for administrators of hospitals and health centers to examine whether their institutions are actually delivering the dignity, responsiveness, accountability and compassion that patients deserve.”
Nicholas Mulbah’s account should not be treated as a final judgment on ELWA Hospital or its medical personnel. It should instead be treated as a warning signal worthy of institutional review and appropriate action in at addressing such situation.
Health authorities could establish mechanisms through which emergency incidents resulting in patient deaths are reviewed, particularly where questions arise concerning triage, response time, referral, communication or availability of treatment.
Families also deserve clear information when a patient dies. Patients deserve to know that someone is listening.
And the poor, the abandoned, the unconscious and those brought to hospitals by strangers deserve the same fundamental attention as everyone else, added a mother of three who only identified to this paper as Aunty Mary.
Moreover, experts say Liberia’s health workers operate under difficult circumstances, often confronting limited resources, heavy workloads and challenging working environments. Their sacrifices should be recognized by appropriate authorities.
But difficult conditions cannot eliminate the need for professional discipline, compassion and accountability.
As Liberia talks about good governance this October, the test should ultimately be visible where citizens need government and public institutions most at the point of service.
For a patient lying critically ill outside a treatment room, good governance is not an abstract principle. It is whether someone responds. It is whether treatment begins. It is whether essential medicine is available. It is whether a health worker cares.
And, sometimes, it can be the difference between a family returning home with a loved one—and a family leaving a hospital compound carrying nothing but grief.
Meanwhile, authorities of the ELWA hospital were not available for comment at the time of the report.
However, in a healthcare advocacy commentary, dated March 30, 2026, styled: “Liberia’s Healthcare Institutions Must Put Life Before Payment,” Dr. Samuel S. P. Quoi pointed out that Liberia is facing a dangerous and deeply troubling reality: critically ill patients are being turned away from hospitals and clinics because of “no bed space,” “no room,” or inability to make immediate payment.
Dr. Quoi wrote that this is not just a system challenge – it is a moral crisis. As a healthcare and public health practitioner, this issue is painfully personal.
He explained: “ My little sister, Leabei Quoi Slawon, and my nephew, an iconic Liberian musician known as “Nyan Dokpa”, were among those who faced barriers to timely care. At the very moment when the healthcare system should have responded with urgency and compassion, doors were closed.
“No bed.”
“No space.”
“No room.”
“What a shame. Medicine is not a business transaction that begins after payment. It is a profession built on sacrifice and the sacred duty to save lives,” Quoi stressed.
According to Dr. Quoi, globally accepted ethical principles are clear: when a life is at risk, treatment must come first.
Turning away critically ill patients violates the very foundation of medical practice. It undermines trust, increases suffering, and, in some cases, contributes directly to preventable deaths.
He stressed in said commentary that Liberia has proven before that it can rise to meet health crises. During Ebola and COVID-19, healthcare workers adapted under extreme conditions.
Hallways became treatment areas. Temporary solutions were created. Lives were saved—not because resources were abundant, but because human life was prioritized. Why are we now doing less when we should be doing more?
If hospitals are overwhelmed, the answer is not refusal; it is adaptation. Emergency triage spaces can be created. Patients can be stabilized while referrals are arranged. The first response should never be to turn a patient away.
Even more concerning is the growing practice of requiring payment before care in emergency situations. While hospitals must operate sustainably, no system should place cost above human life.
He proposed that the Legislature must pass and enforce laws that guarantee emergency treatment for all. The Ministry of Health must establish strict protocols that prevent patient refusal without immediate intervention. The Executive must prioritize healthcare reform that protects the dignity and lives of Liberians. And the Judiciary must ensure accountability where denial of care leads to harm.
Healthcare providers must also reflect. The white coat is not just a symbol of knowledge, it is a symbol of sacrifice and responsibility.
Liberia’s healthcare system will not be judged by its buildings or equipment, but by how it treats its people in their most vulnerable moments We cannot normalize turning patients away.
We cannot accept “no space” as a final answer when a life is at stake. We must act now. Because every life matters. Because no family should endure this pain.
And because when a patient arrives at a hospital in distress, there should only be one response:
Treat first. Save life. Figure out the rest later.




